Categories
Fertility

Common Causes of Female Infertility

Trying to conceive can feel exciting at first. Then months pass, and worry starts to creep in. If that sounds familiar, you are not alone. Many couples face this struggle.

Infertility is often misunderstood. It is not a failure, and it is rarely anyone’s fault. In most cases, there is a medical reason behind it. Finding that reason is the first step toward a solution.

This guide covers the top causes of infertility in women in plain language. You will learn what each one means, what signs to watch for, and when to get help.

This post is part of a larger series. For the full picture on boosting your chances, read our pillar guide: the female fertility guide to boost your chances of conceiving. Use this article to dig deeper into the causes.

This article is for education only. It does not replace advice from your doctor.

What Is Infertility?

Doctors call it infertility when pregnancy does not happen after a set time of trying. The time depends on your age.

  • Under 35: 12 months of regular, unprotected sex
  • 35 to 39: 6 months
  • 40 and older: Talk to a doctor right away

How pregnancy normally happens

Several steps must work together. An ovary releases an egg. The egg travels through a fallopian tube. A sperm meets the egg and fertilizes it. The embryo then attaches to the lining of the uterus.

A problem at any step can make pregnancy harder. That is why causes vary so much from person to person.

Who is affected?

Fertility problems are common. Experts often say about one-third of cases link to the woman. Another third link to the man. The rest involve both partners or have no clear cause.

This means both partners should get checked. Testing one person alone may miss the real issue.

Ovulation Problems

Ovulation problems are among the most common reasons for trouble conceiving. If you do not release an egg each month, pregnancy cannot happen.

Polycystic ovary syndrome (PCOS)

PCOS is a hormone condition. It often causes irregular periods, acne, and extra hair growth. Many women with PCOS ovulate rarely or not at all.

The good news is that PCOS is treatable. Weight management, medicine, and fertility treatments help many women conceive.

Thyroid disorders

Your thyroid controls many body functions. If it is too active or too slow, your cycle can change. Periods may become heavy, light, or absent.

A simple blood test can check your thyroid. Treatment often restores normal ovulation.

High prolactin levels

Prolactin is the hormone that helps make breast milk. When levels run high outside of pregnancy, ovulation can stop. A small, harmless growth in the brain is a common reason.

Medicine usually brings levels back to normal.

Primary ovarian insufficiency

This condition means the ovaries stop working normally before age 40. Periods may become irregular or stop. It can have genetic, immune, or unknown causes.

Early testing matters here. A doctor can explain your options.

Age and Egg Quality

Age is a major factor in fertility. It is also one of the top causes of infertility in women that people feel least able to control.

Why age matters

You are born with all the eggs you will ever have. The number drops over time. The quality of the remaining eggs also declines.

Fertility starts to dip in the early 30s. The drop speeds up after age 35. By the early 40s, natural pregnancy becomes much harder.

Egg quality and miscarriage

Older eggs have a higher chance of chromosome errors. This can make it harder to conceive. It can also raise the risk of miscarriage.

What you can do

You cannot stop the clock. You can, however, take action early.

  • Get a fertility check if you are over 35 and trying
  • Ask about egg freezing if you plan to wait
  • Keep your overall health strong
  • Avoid delays when you suspect a problem

Age is only one piece. Many women in their late 30s and 40s still conceive with the right support.

Deeper dive: Fertility Window: When Are You Most Fertile?

Blocked or Damaged Fallopian Tubes

The fallopian tubes carry the egg to the uterus. If they are blocked or scarred, the egg and sperm cannot meet.

Common reasons for tubal damage

  • Pelvic inflammatory disease (PID), often from untreated infections
  • Sexually transmitted infections such as chlamydia and gonorrhea
  • Past surgery in the belly or pelvis
  • Endometriosis
  • Ectopic pregnancy history

Signs to watch for

Many women feel no symptoms at all. Some notice pelvic pain or unusual discharge. Others only find out after months of trying.

How doctors check

A test called a hysterosalpingogram, or HSG, is common. A doctor places dye into the uterus and takes X-ray images. The images show whether the tubes are open.

Treatment options

Small blockages may be cleared with surgery. When damage is severe, in vitro fertilization (IVF) may help. IVF skips the tubes completely.

Endometriosis

Endometriosis happens when tissue like the uterine lining grows outside the uterus. It can appear on the ovaries, tubes, or other pelvic areas.

Typical symptoms

  • Very painful periods
  • Pain during sex
  • Heavy bleeding
  • Pelvic pain between periods
  • Pain with bowel movements or urination

Some women have no symptoms, so the condition can go unnoticed for years.

How it affects fertility

Endometriosis can cause scar tissue. That scar tissue may twist or block the tubes. It can also harm the ovaries and affect egg quality.

Inflammation may play a role too. It can make it harder for an embryo to attach.

Getting a diagnosis

Doctors may use an ultrasound or MRI. Sometimes a small surgery called laparoscopy is needed to confirm it.

Treatment

Options include pain medicine, hormone therapy, and surgery to remove tissue. Many women conceive after treatment. Others use IVF.

Uterus and Cervix Problems

The uterus must be healthy to hold a pregnancy. Some shape or growth problems can get in the way.

Fibroids

Fibroids are non-cancer growths in the uterine wall. Many cause no trouble. Some, especially those inside the uterine cavity, can block implantation.

Polyps

Polyps are small growths on the uterine lining. They can cause irregular bleeding. They may also reduce the chance of an embryo attaching.

Uterine shape differences

Some women are born with a uterus that has a wall in the middle. This is called a septum. Others have a heart-shaped uterus. These differences can raise miscarriage risk.

Scar tissue

Past surgery or infection can cause scar tissue inside the uterus. This is called Asherman’s syndrome. It may lead to light or missed periods.

Cervical issues

The cervix makes mucus that helps sperm travel. If it is narrow or damaged, sperm may struggle to pass. Past procedures can sometimes cause this.

Many of these problems are fixable with minor surgery.

Lifestyle Factors

Daily habits can affect your hormones and egg health. These changes are often within your control.

Body weight

Being very underweight or overweight can disrupt ovulation. Fat tissue affects hormone levels. Even a modest change in weight can restore regular cycles for some women.

Smoking

Smoking harms eggs and speeds up egg loss. It also raises the risk of miscarriage. Quitting is one of the best steps you can take.

Alcohol and caffeine

Heavy drinking can lower fertility. Many doctors suggest cutting back or stopping while you try. Keep caffeine moderate as well.

Stress and sleep

Stress alone rarely causes infertility. But long-term stress can change your cycle. Poor sleep may also affect hormones.

Extreme exercise

Very intense workouts can stop periods in some women. Balance is key. Regular, moderate movement is usually best.

Diet

A balanced diet supports hormone health. Focus on whole foods, fiber, healthy fats, and enough protein. Avoid crash diets.

For a deeper look at healthy habits, see our female fertility guide.

Medical Conditions and Medicines

Some health conditions and treatments can affect fertility. Many women do not link them to their struggle.

Conditions that may play a role

  • Type 1 and type 2 diabetes
  • Celiac disease
  • Autoimmune diseases such as lupus
  • Chronic kidney or liver disease
  • Some genetic conditions

Cancer treatment

Chemotherapy and radiation can damage the ovaries. If you face treatment, ask about fertility preservation first. Options like egg or embryo freezing may be possible.

Medicines

Some drugs can change ovulation or hormone levels. Examples include certain anti-inflammatory drugs and some mental health medicines. Never stop a medicine without talking to your doctor.

Infections

Untreated infections can harm the reproductive organs. Regular screening and early treatment protect your fertility.

Unexplained Infertility

Sometimes tests show no clear cause. This is called unexplained infertility. It affects a good number of couples.

Why it happens

Current tests cannot spot every issue. Subtle problems with egg quality or embryo attachment may go undetected.

Is there still hope?

Yes. Many couples with unexplained infertility do conceive. Options include timed intercourse, medicines to boost ovulation, intrauterine insemination (IUI), and IVF.

Staying patient

This diagnosis can feel frustrating. You may want a clear answer. Lean on your doctor and support network. Counseling can help during this time.

When to See a Doctor

Do not wait too long. Early help gives you more choices.

  1. You are under 35 and have tried for 12 months.
  2. You are 35 to 39 and have tried for 6 months.
  3. You are 40 or older and want to conceive.
  4. Your periods are very irregular or absent.
  5. You have severe period or pelvic pain.
  6. You have had repeated miscarriages.
  7. You have a known issue like endometriosis or PCOS.

Tests you may expect

  • Blood tests for hormones
  • Ultrasound of the pelvis
  • HSG to check the tubes
  • Ovarian reserve tests
  • Semen analysis for your partner

Testing is usually simple and gives useful answers.

Treatment Options at a Glance

Treatment depends on the cause, your age, and your goals. Your doctor will build a plan with you.

Common options

  • Lifestyle changes: Better sleep, balanced diet, healthy weight
  • Ovulation medicines: Pills or injections that help release eggs
  • Surgery: To remove fibroids, polyps, scar tissue, or endometriosis
  • IUI: Sperm is placed directly into the uterus
  • IVF: Eggs and sperm are joined in a lab, then placed in the uterus

Emotional support

The journey can be tough. Many people feel stress, guilt, or sadness. These feelings are normal. Talk with your partner, a counselor, or a support group.

Final Thoughts

Infertility is common, and there are many possible reasons. The top causes of infertility in women include ovulation problems, age, blocked tubes, endometriosis, and uterine issues. Lifestyle habits and health conditions can add to the mix.

The key is not to wait in silence. Book a visit, get tested, and learn your options. Most causes can be treated or managed.

Remember that knowing the top causes of infertility in women is only the start. A clear diagnosis leads to a clear plan. Keep reading our female fertility guide for more steps you can take today.

FAQs

  1. What is the most common reason women have trouble getting pregnant?

Ovulation problems are among the most common. PCOS and thyroid issues are frequent examples.

  1. Can stress cause infertility?

Stress alone rarely causes infertility. Long-term stress can change your cycle, though, which may make conception harder.

  1. How do I know if I am ovulating?

Regular periods are a good sign. Ovulation kits, cycle tracking, and blood tests can also help confirm it.

  1. Does age really affect fertility that much?

Yes. Egg numbers and quality drop over time. The decline becomes faster after age 35.

  1. Can I get pregnant with PCOS?

Yes. Many women with PCOS conceive with lifestyle changes, medicine, or fertility treatments.

  1. Can endometriosis be cured?

There is no permanent cure. Treatments can ease symptoms and improve your chance of pregnancy.

Categories
Fertility

The Menstrual Cycle and Fertility: A Complete Breakdown

Ever notice how some weeks you feel unstoppable, and others you just want a blanket and a snack? Your hormones are behind those swings. They also decide the days when you can get pregnant.

Whether you want to conceive, avoid pregnancy, or simply understand your body, this guide helps. It gets menstrual cycle phases and fertility explained in plain words, with no medical jargon. Grab a cup of tea and let’s get started.

What Is the Menstrual Cycle?

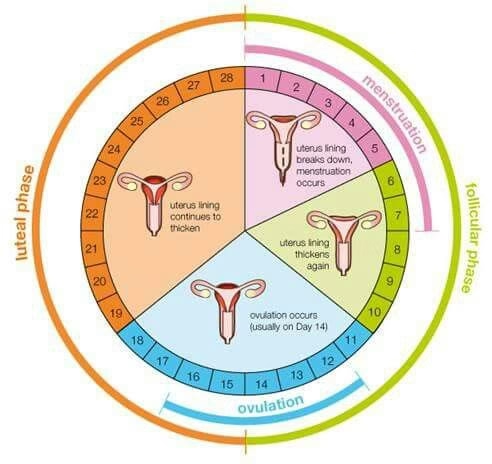
The menstrual cycle is the monthly series of changes your body goes through to prepare for a possible pregnancy. It starts on the first day of your period. It ends the day before your next period begins.

Many people think a cycle lasts 28 days. That’s just the average. Anywhere from 21 to 35 days is common for adults. Your own length may shift a little from month to month, and that’s normal.

Four hormones run the show:

  • Estrogen: builds up the uterine lining and helps an egg mature.
  • Progesterone: keeps the lining thick and ready for a fertilized egg.
  • Follicle-stimulating hormone (FSH): wakes up the follicles in your ovaries.
  • Luteinizing hormone (LH): triggers the release of an egg.

Think of these hormones as a team passing a baton. When one rises, another falls, and the cycle moves forward. Once you understand this rhythm, your fertility starts to make a lot more sense.

The Four Phases of Your Cycle

Each cycle has four phases. Here are the menstrual cycle phases and fertility explained step by step.

Phase 1: The Menstrual Phase (Days 1–5)

This phase starts on day one of your period. Your uterus sheds its lining because pregnancy didn’t happen. That’s the bleeding you see.

Periods usually last three to seven days. Hormone levels sit at their lowest now, so you may feel tired. Cramps, headaches, and back pain are common too.

Can you get pregnant during your period? It’s unlikely, but it’s not impossible. Sperm can live up to five days inside the body. If your cycle is short, you might ovulate soon after your period ends. That overlap can lead to pregnancy.

A few small habits can make this phase easier. Rest when you can and drink plenty of water. Try gentle movement, like a short walk. A heating pad can also ease cramps.

Phase 2: The Follicular Phase (Days 1–13)

This phase overlaps with your period. It starts on day one and lasts until ovulation. FSH rises and tells your ovaries to grow several follicles. Each follicle holds an immature egg.

Usually, one follicle becomes the dominant one. The others fade away. As that follicle grows, it releases more estrogen. Estrogen rebuilds the uterine lining after your period.

Many people feel a boost during this time. Energy rises, mood lifts, and skin often looks clearer. That’s estrogen at work.

For fertility, this phase decides how ready your egg will be. It’s also the part of your cycle that varies the most in length. That’s why one person has a 24-day cycle and another has a 34-day cycle. Stress, illness, and travel can stretch this phase out.

Phase 3: Ovulation (Around Day 14)

Ovulation is the star of the show. A surge of LH makes the dominant follicle burst open. It releases a mature egg into the fallopian tube.

This usually happens about 12 to 16 days before your next period. It doesn’t always fall on day 14. If your cycle is 35 days long, ovulation will come later.

The egg lives only 12 to 24 hours after release. That’s a tiny window. Still, sperm can survive for up to five days. So you can get pregnant from sex that happens before ovulation.

Here are signs that ovulation is close:

  • Clear, stretchy cervical mucus, like raw egg white
  • A mild twinge on one side of your lower belly
  • A higher sex drive
  • Slight breast tenderness

Phase 4: The Luteal Phase (Days 15–28)

After ovulation, the empty follicle turns into a structure called the corpus luteum. It makes progesterone. This hormone thickens the uterine lining so it’s ready for a fertilized egg.

If the egg is fertilized, it travels to the uterus. It usually implants about six to ten days after ovulation. Your body then makes the pregnancy hormone hCG. That’s what a pregnancy test picks up.

If there’s no fertilization, the corpus luteum breaks down. Progesterone and estrogen drop. Your lining sheds, and a new cycle begins.

The luteal phase usually lasts 12 to 14 days. It tends to stay steady from cycle to cycle. Many people notice PMS symptoms now, such as bloating, mood swings, cravings, and sore breasts. Progesterone causes most of them.

If your luteal phase is shorter than ten days, the lining may not have enough time to support an embryo. A doctor can check this for you.

How Each Phase Affects Your Mood and Body

Your hormones don’t just control fertility. They also shape how you feel day to day. Knowing this can save you a lot of self-blame.

During your period, energy is low. Your body is working hard, so go easy on yourself. In the follicular phase, estrogen climbs and you may feel more social, creative, and focused.

Around ovulation, many people feel their best. Confidence and energy often peak. Some also notice a stronger sex drive.

In the luteal phase, progesterone takes over. You may feel calmer at first, then more tired or moody as your period nears. Sleep can get lighter too.

You don’t have to plan your life around your cycle. But small tweaks help. Save big presentations for your high-energy days if you can. Plan rest, comfort food, and early nights for the days before your period.

Your Fertile Window Explained

Your fertile window is the stretch of days when pregnancy is possible. It lasts about six days. It includes the five days before ovulation and the day of ovulation itself.

Why six days? Sperm can survive up to five days, and the egg lives about one day. Chances are highest on the two days before ovulation and on ovulation day.

Here’s the catch. Ovulation rarely happens on the exact same day each month. So counting days on a calendar is only a guess. Tracking real body signs gives you a much better picture.

If you’re trying to conceive, aim to have sex every one to two days during this window. You don’t need to be perfect. Regular sex in these days gives you a good chance.

If you want to avoid pregnancy, remember that the calendar method alone isn’t reliable. Pair it with a proven method, such as condoms. Or talk to a doctor about other options.

How to Track Your Cycle and Ovulation

You don’t need fancy gadgets. Start simple and add tools as you go. Here are the most popular methods.

  1. Calendar tracking. Mark the first day of every period. After three months, you’ll see your average cycle length.
  2. Basal body temperature (BBT). Take your temperature every morning before you get out of bed. It rises by about 0.3 to 0.6°C after ovulation. This confirms ovulation happened, but it doesn’t predict it.
  3. Cervical mucus checks. Notice the texture each day. Egg-white mucus signals peak fertility.
  4. Ovulation predictor kits (OPKs). These urine strips detect the LH surge. Ovulation usually follows within 24 to 36 hours.
  5. Fertility apps. Apps pull your data together and estimate your window. Treat their predictions as a guide, not a promise.

For best results, combine two or three methods. For example, use OPKs along with cervical mucus checks. Track for at least three cycles to see a clear pattern.

What Your Cycle Length Tells You

Your cycle length is a handy clue about your health. A steady cycle often means your hormones are working well. A cycle that jumps around by more than seven or eight days can hint at irregular ovulation.

Short cycles may mean you ovulate early. Long cycles may mean ovulation comes late, or sometimes not at all. Neither is a problem on its own. But a clear pattern over several months is worth sharing with your doctor.

Keep a simple note each month. Write down your start date, how heavy the flow was, and any pain or mood changes. These details help a doctor spot patterns fast.

What Can Change Your Cycle

Your cycle isn’t set in stone. Many everyday things can nudge it off track.

Lifestyle Factors

Stress is a big one. High stress raises cortisol, which can delay or even stop ovulation. Poor sleep, intense exercise, and sudden weight changes can do the same. Being very underweight or overweight can also affect your hormones.

Travel, night shifts, and illness can shift your timing too. Usually, your cycle returns to normal once life settles down.

Medical Conditions

Some health conditions affect cycles and fertility:

  • Polycystic ovary syndrome (PCOS): causes irregular or missed ovulation.
  • Thyroid disorders: an overactive or underactive thyroid can change your cycle length.
  • Endometriosis: tissue grows outside the uterus and can cause pain and fertility trouble.
  • Primary ovarian insufficiency: the ovaries slow down before age 40.

These conditions are common and treatable. Early diagnosis makes a big difference.

Age and Life Stages

Fertility is highest in your 20s. It starts to dip in the early 30s and drops faster after 35. In the years before menopause, called perimenopause, cycles often get shorter or more irregular.

Hormonal birth control also changes your natural pattern. It can take a few months to settle after you stop.

When to Talk to a Doctor

Some changes are normal. Others deserve a check-up. See a healthcare provider if:

Your periods stop for three months or more, and you’re not pregnant

  • Your cycles are shorter than 21 days or longer than 35 days most of the time
  • Bleeding is very heavy, and you soak a pad or tampon every hour or two
  • Pain is severe and stops you from doing daily tasks
  • You’re under 35 and haven’t conceived after 12 months of trying
  • You’re 35 or older and haven’t conceived after six months

Don’t wait if something feels wrong. You know your body best. A simple blood test or ultrasound can often give answers quickly.

Simple Ways to Support Your Fertility

You can’t control everything, but small habits help.

Eat balanced meals with plenty of vegetables, whole grains, healthy fats, and protein. Iron-rich foods replace what you lose during periods. Folate matters too, especially if you plan to get pregnant. Many doctors recommend a folic acid supplement before conception.

Move your body regularly, but don’t overdo it. Moderate exercise like walking, yoga, or cycling supports hormone balance. Aim for seven to nine hours of sleep each night. Manage stress with whatever works for you, such as journaling, music, or time outdoors.

Limit alcohol and skip smoking. Both can harm egg quality and hormone levels. Keep up with regular health checks, including thyroid tests when your doctor advises them.

Common Myths About Cycles and Fertility

Let’s clear up a few popular myths.

  • Myth: Everyone ovulates on day 14. Truth: Timing depends on your cycle length and changes from month to month.
  • Myth: You can’t get pregnant on your period. Truth: It’s rare, but it can happen, especially with shorter cycles.
  • Myth: A regular period means you ovulate. Truth: Not always. You can bleed without releasing an egg.
  • Myth: Irregular cycles mean you can’t conceive. Truth: Many people with irregular cycles get pregnant, sometimes with extra support.

To know more on Fertility, please read our complete guide Female Fertility Guide: Boost Your Chances of Conceiving.

Final Thoughts

Your cycle is more than a monthly period. It’s a reliable sign of how your body is doing. Now that you have menstrual cycle phases and fertility explained, you can track your pattern with confidence.

Start with one simple method this month. Mark your period dates and notice how you feel each week. After a few cycles, you’ll spot your own rhythm. If something seems off, talk to a doctor. You deserve clear answers.

Disclaimer: This article is for general education only. It isn’t medical advice. Please talk to a qualified healthcare provider about your own health.


FAQs

How many phases are there in the menstrual cycle?

There are four: menstrual, follicular, ovulation, and luteal. Each one has its own hormone pattern and symptoms.

When am I most fertile during my cycle?

You’re most fertile in the two days before ovulation and on ovulation day. The whole fertile window lasts about six days.

Can I get pregnant right after my period ends?

Yes, it’s possible. Sperm can live up to five days, so early ovulation can overlap with the end of your period. This is more likely with short cycles.

How long is a normal menstrual cycle?

Most adults have cycles between 21 and 35 days. A little variation from month to month is normal.

What is the best way to track ovulation?

Combining methods works best. Try cervical mucus checks, ovulation predictor kits, and basal body temperature together for the clearest picture.

Does stress affect ovulation?

Yes. High stress can delay or even stop ovulation, which makes your cycle longer or irregular.

When should I see a doctor about my cycle?

See a doctor if your periods stop for three months, your cycles are very irregular, or your pain is severe. Also seek help if you haven’t conceived after 12 months of trying, or six months if you’re 35 or older.

Categories
Health

Which Size of Uterine Fibroid Is Dangerous

Hearing that you have uterine fibroids can be unsettling. For many women, the first question that comes to mind is simple but important: how big is too big?

It’s natural to assume that size alone determines whether fibroids are dangerous. But the truth is a bit more nuanced. Size does matter, but it’s not the only factor. The location, number, and symptoms of fibroids all play a role in determining how serious they are.

Let’s walk through this in a clear, practical way so you can understand what really matters when it comes to uterine fibroids.

What Are Uterine Fibroids?

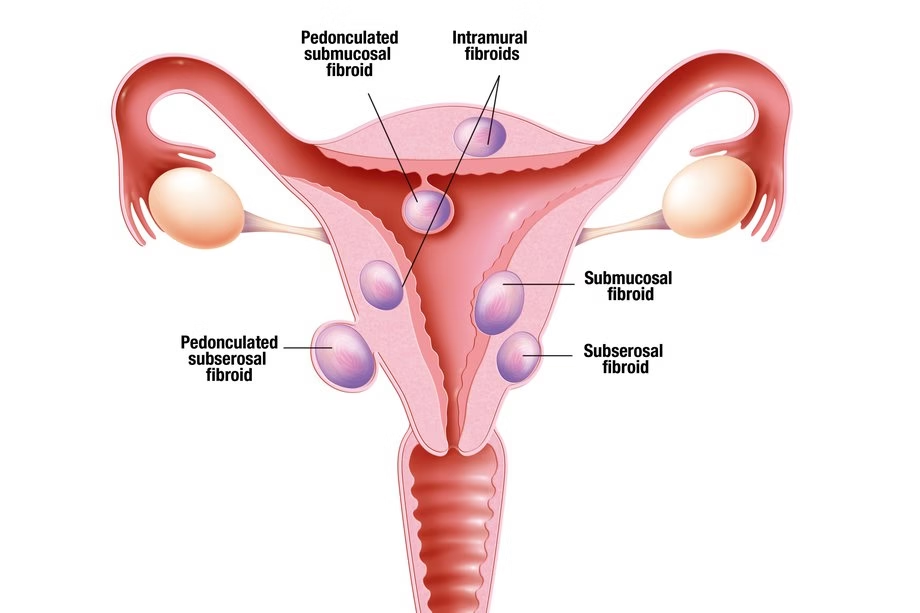
Uterine fibroids are non-cancerous growths that develop in or around the uterus. They are quite common and can occur at any age during a woman’s reproductive years.

Some women may have small fibroids and never even know it. Others may experience noticeable symptoms that affect daily life.

Fibroids can vary widely in size, from very small, almost undetectable growths to large masses that can change the shape of the uterus.

Which Size of Uterine Fibroid Is Dangerous?

This is where things often get confusing.

There isn’t a single size that automatically makes a fibroid dangerous. Instead, doctors look at a combination of size, symptoms, and location.

That said, fibroids are often grouped into general size categories to help understand their potential impact.

Small fibroids

  • Usually less than a few centimeters
  • Often do not cause symptoms
  • Typically monitored without treatment

Medium fibroids

  • Can start causing noticeable symptoms
  • May lead to heavier periods or pelvic discomfort

Large fibroids

  • More likely to cause complications
  • Can press on nearby organs
  • May affect fertility or pregnancy

In general, larger fibroids have a higher chance of causing problems, but even small fibroids can be troublesome if they are located in sensitive areas of the uterus.

Why Size Alone Doesn’t Tell the Whole Story

It’s possible to have a relatively small fibroid that causes significant symptoms, while a larger one might go unnoticed.

This happens because location plays a key role.

For example:

  • A fibroid inside the uterine cavity can affect menstrual flow and fertility even if it is small
  • A fibroid on the outer wall may grow larger without causing major symptoms

So when asking whether uterine fibroids are dangerous, the better question is how they are affecting your body, not just how big they are.

Uterine Fibroids Symptoms to Watch For

Fibroids can present in different ways depending on their size and position.

Common uterine fibroids symptoms include:

  • Heavy or prolonged menstrual bleeding
  • Pelvic pain or pressure
  • Frequent urination due to pressure on the bladder
  • Constipation if the bowel is affected
  • Pain during intercourse
  • Lower back discomfort

Some women may also experience fatigue due to blood loss from heavy periods.

If symptoms are severe or persistent, it may indicate that the fibroid is causing complications.

When Do Fibroids Become Dangerous?

Fibroids are generally not life-threatening, but they can become serious in certain situations.

Severe bleeding

  • Heavy periods can lead to anemia
  • Symptoms may include fatigue, weakness, and dizziness

Rapid growth

  • Sudden increase in size may require evaluation
  • Though fibroids are usually benign, rapid growth needs medical attention

Pressure on organs

  • Large fibroids can press on the bladder or intestines
  • This can lead to urinary or digestive problems

Fertility issues

  • Fibroids inside the uterus can interfere with implantation
  • May increase the risk of miscarriage

Pregnancy complications

  • Depending on size and location, fibroids can affect fetal position or growth

These are the situations where fibroids move from being a mild condition to something that requires active management.

Uterine Fibroids Causes

The exact cause of fibroids is not fully understood, but several factors are believed to contribute.

  • Hormonal influence, especially estrogen and progesterone
  • Genetic factors and family history
  • Growth factors that regulate tissue development
  • Lifestyle factors such as diet and weight

Fibroids tend to grow during reproductive years and may shrink after menopause due to hormonal changes.

Are Uterine Fibroids Dangerous?

For most women, fibroids are not dangerous in the sense of being life-threatening.

However, they can significantly impact quality of life if symptoms are severe.

The key concern is not cancer risk, since fibroids are almost always benign, but rather how they affect:

With proper monitoring and treatment, complications can usually be managed effectively.

Do Uterine Fibroids Go Away?

This is a common question.

Fibroids do not usually disappear on their own during reproductive years. However, they may shrink naturally after menopause when hormone levels decrease.

In some cases:

  • Small fibroids remain stable and do not grow
  • Symptoms may improve over time
  • Medical treatment can help control growth

So while they may not fully go away, they can become less problematic depending on the situation.

Treatment for Uterine Fibroids

Treatment depends on symptoms, size, and personal health goals.

Watchful waiting

  • Suitable for small, symptom-free fibroids
  • Regular monitoring through checkups

Medications

  • Help control symptoms such as heavy bleeding
  • May temporarily shrink fibroids

Minimally invasive procedures

  • Techniques to reduce or remove fibroids without major surgery

Surgical options

  • Removal of fibroids while preserving the uterus
  • In severe cases, removal of the uterus may be considered

The right approach depends on individual needs, especially if pregnancy is planned.

Fibroids and Pregnancy

Many women with fibroids have healthy pregnancies.

However, certain fibroids can increase risks depending on their size and location.

Possible concerns include:

  • Difficulty with implantation
  • Increased risk of miscarriage
  • Preterm labor in some cases
  • Changes in fetal position

Regular prenatal care helps manage these risks effectively.

When Should You See a Doctor?

It’s important to seek medical advice if you notice:

  • Very heavy or prolonged periods
  • Persistent pelvic pain
  • Rapid abdominal enlargement
  • Difficulty with urination or bowel movements
  • Trouble conceiving

Early evaluation helps prevent complications and provides more treatment options.

Practical Takeaway

If you’re wondering which size of uterine fibroid is dangerous, the answer is not as simple as a number.

What truly matters is:

  • Whether the fibroid is causing symptoms
  • Where it is located
  • How it is affecting your daily life or reproductive health

Large fibroids are more likely to cause issues, but even small ones can be problematic in certain situations.

Final Thoughts

Uterine fibroids are common, and in many cases, they are manageable without major intervention.

Understanding the relationship between size, symptoms, and overall health is key to making informed decisions.

If you’ve been diagnosed with fibroids, focus on how your body feels rather than just the measurements. With proper care and guidance, most women are able to manage fibroids effectively and maintain a good quality of life.

Categories
PCOS

Polycystic Ovary Syndrome (PCOS): Symptoms, Causes, and Treatment Options

The Complete Guide to PCOS: Symptoms, Causes, Types, and Treatment

Polycystic Ovary Syndrome is one of the most common hormonal conditions affecting women of reproductive age — and one of the most misunderstood. It is estimated to affect between 8% and 13% of women worldwide, yet millions go undiagnosed for years, cycling through frustrating symptoms without a clear explanation.

This guide is the most complete resource on this site for understanding PCOS. It covers what the condition actually is, why it happens, how it shows up differently in different women, how it is diagnosed, and what genuine management looks like — both medically and through lifestyle. Every major section links out to a dedicated in-depth guide so you can go as deep as you need on any specific aspect of the condition.

If you have recently been diagnosed, if you suspect you might have PCOS, or if you simply want to understand the condition more thoroughly, start here.

Table of Contents

  • What Is PCOS
  • PCOS vs PCOD — What Is the Difference
  • The 4 Types of PCOS
  • How PCOS Affects Your Entire Body
  • Common Symptoms of PCOS
  • Hidden and Overlooked Symptoms
  • What Causes PCOS
  • How PCOS Is Diagnosed
  • PCOS and Mental Health
  • PCOS and Diet and Nutrition
  • PCOS and Fertility
  • Treatment Options for PCOS
  • Long-Term Health Risks of PCOS
  • Living Well With PCOS
  • Frequently Asked Questions

What Is PCOS?

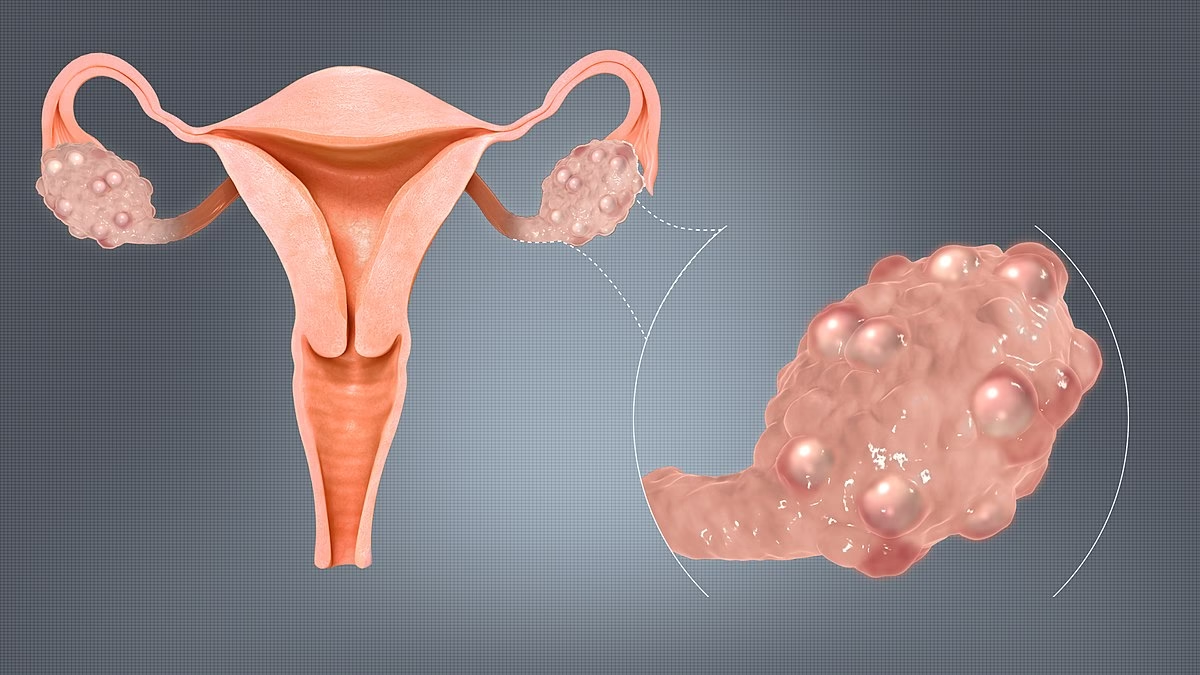
PCOS (Polycystic Ovary Syndrome) is a hormonal disorder in which the ovaries produce an abnormal amount of androgens — often called male hormones — disrupting the normal process of ovulation. This imbalance can lead to irregular or absent menstrual cycles, the development of multiple small follicles in the ovaries, and a wide range of symptoms that extend far beyond reproductive health.

Despite its name, you do not need to have ovarian cysts to be diagnosed with PCOS. The cysts described in the name are not true cysts — they are immature follicles that failed to release an egg and collected in the ovary. Many women diagnosed with PCOS have no visible follicles on ultrasound, while some women with follicles on ultrasound do not have the condition.

PCOS is not a single, uniform disease. It is a syndrome — meaning it presents differently from person to person depending on which underlying mechanisms are driving it. This is why treatment that works well for one woman may do little for another, and why understanding your specific type matters.

PCOS vs PCOD — What Is the Difference

These two terms are frequently confused, and in some regions used interchangeably, but they refer to different things.

PCOD (Polycystic Ovary Disease) refers specifically to a structural finding — the presence of multiple cysts in the ovaries. It is considered a milder condition in which the ovaries release immature eggs that accumulate as cysts. Lifestyle changes alone can often manage PCOD effectively, and it does not always cause the same degree of hormonal disruption.

PCOS is a broader endocrine disorder involving hormonal imbalance, disrupted ovulation, and androgen excess. It has wider systemic effects on metabolism, mental health, cardiovascular health, and fertility. PCOS typically requires more comprehensive management.

A woman can have PCOD without PCOS, but PCOS generally includes the ovarian changes associated with PCOD alongside more significant hormonal disruption.

The 4 Types of PCOS

Not all PCOS cases are driven by the same underlying mechanism. Understanding which type you are dealing with is one of the most important steps toward effective management, because the root cause shapes both the symptoms and the best response.

Insulin-Resistant PCOS

This is the most common type, affecting the majority of women with PCOS. It occurs when the body’s cells stop responding efficiently to insulin, causing the pancreas to produce more. Elevated insulin levels signal the ovaries to produce excess androgens, which disrupts ovulation and triggers the characteristic symptoms of PCOS.

Typical signs include difficulty losing weight, intense sugar cravings, energy crashes after meals, fatigue, irregular periods, and dark patches of skin on the neck or underarms (a condition called acanthosis nigricans). Women with this type have a higher risk of developing type 2 diabetes over time.

Inflammatory PCOS

In this type, chronic low-grade inflammation drives androgen production. The inflammation can be triggered by dietary factors, gut health issues, environmental toxins, or an underlying autoimmune response. The immune system remains in a low-level state of activation that continuously stimulates the ovaries.

Symptoms often include persistent fatigue, unexplained headaches, skin issues, joint discomfort, and digestive problems alongside the hormonal symptoms of PCOS. Blood tests may show elevated inflammatory markers such as CRP (C-reactive protein).

Adrenal PCOS

Adrenal PCOS is driven not by the ovaries but by the adrenal glands. When the adrenal glands are under chronic stress, they overproduce androgens — particularly DHEA-S (dehydroepiandrosterone sulfate) — independently of insulin levels.

This type is often seen in women under significant and prolonged stress, and is closely connected to HPA axis dysregulation. Unlike insulin-resistant PCOS, women with adrenal PCOS often have normal insulin levels, normal weight, and may not respond to the dietary interventions that help other types. Stress management, nervous system regulation, and adrenal support are central to managing this type.

Post-Pill PCOS

This type can emerge after stopping hormonal contraceptives. Birth control pills suppress the body’s natural hormone production. When they are discontinued, the hormonal system must restart — and for some women, this recalibration process goes wrong, producing a temporary surge in androgens and PCOS-like symptoms.

Symptoms typically include irregular periods, acne, and hair shedding in the months following discontinuation. In many cases, post-pill PCOS resolves on its own within three to six months. However, for some women the underlying hormonal dysregulation was already present before the pill and was simply being masked by it.

For a complete breakdown of all four types including how to identify which one applies to you, see our dedicated guide: The 4 Types of PCOS Explained.

How PCOS Affects Your Entire Body

PCOS is not a condition confined to the ovaries. It is a full-body endocrine disorder that affects multiple systems simultaneously.

Hormonal System

The hormonal disruption in PCOS is multidimensional. Elevated androgens suppress normal ovulation. LH (luteinizing hormone) levels are often disproportionately high relative to FSH (follicle-stimulating hormone), throwing off the signals the ovaries need to release eggs regularly. In some women, cortisol and prolactin are also affected. This is why symptoms can appear across so many apparently unrelated areas — the hormonal system influences nearly every function in the body.

Metabolic System

Insulin resistance is present in up to 70% of women with PCOS, regardless of body weight. When the body produces excess insulin to compensate, it fuels a cycle of fat storage (particularly around the abdomen), increased androgen production, and energy dysregulation. Over time, this metabolic disruption significantly raises the risk of type 2 diabetes, fatty liver disease, and metabolic syndrome.

Reproductive System

PCOS directly impairs the ovulation process. When ovulation is irregular or absent, the uterine lining does not shed normally, leading to irregular or missed periods. Immature follicles may accumulate in the ovaries. The combination of anovulation (absent ovulation) and hormonal imbalance is the primary reason PCOS is one of the leading causes of female infertility — though it is important to note that many women with PCOS conceive successfully with appropriate support.

Skin and Hair

Excess androgens cause several visible changes. Acne — particularly along the jawline, chin, and cheeks — is one of the most common presenting symptoms. Hirsutism (excess hair growth on the face, chest, or back) affects a significant proportion of women with PCOS. Simultaneously, androgenic alopecia (hair thinning on the scalp) can occur. Skin darkening in body folds (acanthosis nigricans) is a sign of insulin resistance.

Mental Health

PCOS significantly increases the risk of anxiety and depression. The hormonal fluctuations, physical symptoms, fertility concerns, and metabolic disruption all contribute to psychological burden. This relationship is bidirectional — stress and emotional distress worsen hormonal imbalance, which worsens mental health symptoms, creating a loop that is difficult to break without addressing both dimensions simultaneously.

For a full exploration of how PCOS affects mental health, see: Emotional Symptoms of PCOS You Shouldn’t Ignore.

Common Symptoms of PCOS

Symptoms vary considerably in severity and presentation from person to person, which is one reason diagnosis is often delayed.

The most commonly reported symptoms include:

  • Irregular, infrequent, or absent menstrual cycles
  • Excess hair growth on the face, chest, or back (hirsutism)
  • Acne, particularly along the jawline and chin
  • Hair thinning or loss on the scalp
  • Weight gain, especially concentrated around the abdomen
  • Difficulty losing weight despite diet and exercise
  • Skin darkening in folds of the neck, groin, or under the breasts
  • Fatigue and persistent low energy
  • Mood swings, anxiety, or depression
  • Difficulty conceiving

For a complete list of symptoms including the less commonly discussed ones, see: Signs of Hormonal Imbalance PCOS You Shouldn’t Ignore.

Hidden and Overlooked Symptoms

Many PCOS symptoms are either dismissed as unrelated or normalized as stress or aging. Several deserve more attention than they typically receive.

Brain fog — difficulty concentrating, poor short-term memory, and mental fatigue — is reported by a significant number of women with PCOS but rarely discussed in clinical settings. It is linked to both insulin resistance and chronic inflammation affecting cognitive function.

Sleep disturbances and obstructive sleep apnea are more common in women with PCOS than in the general population, even in those who are not higher weight.

Gut health issues including bloating, irregular digestion, and sensitivity to certain foods are increasingly recognized as connected to the inflammatory component of PCOS.

Pelvic pain outside of the menstrual cycle can occur and is sometimes mistaken for other conditions.

For a deeper look at the symptoms most people overlook, see: The Hidden Symptoms of PCOS No One Talks About.

What Causes PCOS

The exact cause of PCOS is not yet fully understood. It is considered a multifactorial condition — meaning no single trigger causes it, but rather a combination of genetic, environmental, and lifestyle factors.

Genetic Predisposition

PCOS runs in families. Women with a mother or sister who has PCOS are significantly more likely to develop it themselves. Several genes involved in hormone production, insulin signaling, and inflammatory pathways have been linked to PCOS, though no single “PCOS gene” has been identified.

Hormonal Imbalance

Elevated androgens are both a cause and a consequence of PCOS. High androgen levels prevent normal follicle maturation and ovulation, which in turn leads to more androgen production — a self-reinforcing cycle.

Insulin Resistance

For many women, insulin resistance is not just a consequence of PCOS — it is a contributing driver. High insulin levels directly stimulate ovarian androgen production, and the resulting hormonal imbalance worsens insulin resistance further.

For a deep dive into this mechanism, see: Root Cause of PCOS Hormonal Imbalance.

Chronic Inflammation

Low-grade systemic inflammation can activate androgen-producing pathways in the ovaries independently of insulin levels. Diet, gut microbiome health, stress, and environmental exposures all influence the body’s inflammatory state.

Stress and the HPA Axis

Chronic psychological or physical stress activates the HPA (hypothalamic-pituitary-adrenal) axis, elevating cortisol and adrenal androgens. For women with adrenal PCOS, this is the primary driver of the condition.

For a full explanation of the stress-PCOS connection, see: Can Stress Cause PCOS.

Early Life and Developmental Factors

Emerging research suggests that early-life exposures — including prenatal androgen exposure, childhood trauma, and early-onset puberty — may predispose girls to developing PCOS later in life. This is an area of active research that is reshaping how clinicians think about PCOS prevention.

How PCOS Is Diagnosed

There is no single test that confirms PCOS. Diagnosis is made through a combination of criteria, clinical evaluation, and investigations to rule out other conditions.

Rotterdam Criteria

The most widely used diagnostic framework is the Rotterdam Criteria, which requires at least two of the following three features to be present:

  • Irregular or absent ovulation, typically reflected in irregular periods
  • Clinical or biochemical signs of elevated androgens (acne, hirsutism, hair loss, or elevated testosterone on blood test)
  • Polycystic ovaries on pelvic ultrasound

Meeting two out of three is sufficient for diagnosis — you do not need all three.

Blood Tests

A comprehensive hormone panel typically includes testosterone and DHEA-S (androgen levels), LH and FSH ratio, fasting insulin and glucose, thyroid function, prolactin levels, and sometimes AMH (anti-Müllerian hormone), which correlates with follicle count.

Pelvic Ultrasound

A transvaginal or abdominal ultrasound examines the ovaries for the presence of multiple small follicles and any increase in ovarian volume. The current threshold used in many guidelines is twelve or more follicles per ovary, or an ovarian volume greater than ten milliliters.

Ruling Out Other Conditions

Because PCOS shares symptoms with several other conditions, diagnosis also involves ruling out thyroid disorders, hyperprolactinemia (elevated prolactin), congenital adrenal hyperplasia, Cushing’s syndrome, and other causes of androgen excess.

For a complete guide on what to expect when getting tested, see: How Is PCOS Diagnosed.

PCOS and Mental Health

The psychological burden of PCOS is consistently underestimated in clinical settings. Research shows that women with PCOS are significantly more likely to experience anxiety, depression, and disordered eating compared to women without the condition.

This is not simply a reaction to dealing with a chronic condition. The hormonal imbalances themselves — particularly elevated androgens and cortisol — directly influence mood regulation and stress response. Insulin resistance affects energy levels and cognitive function. The physical symptoms (acne, hair changes, weight fluctuations) carry significant emotional weight and impact body image and self-esteem.

The relationship is bidirectional. PCOS worsens mental health, and poor mental health worsens PCOS. Breaking this cycle often requires addressing both dimensions — not treating the hormonal issues in isolation from the emotional ones.

If you are experiencing persistent anxiety or low mood alongside PCOS symptoms, this deserves attention as part of your overall care plan, not as a separate issue.

For more on this topic, see: Emotional Symptoms of PCOS You Shouldn’t Ignore and Can Stress Cause PCOS.

PCOS and Diet and Nutrition

Diet is one of the most powerful levers available for managing PCOS — particularly for women with insulin-resistant and inflammatory types. What you eat directly affects insulin levels, androgen production, and the inflammatory environment that drives symptoms.

Principles of a PCOS-Supportive Diet

The core dietary approach for PCOS focuses on stabilizing blood sugar, reducing chronic inflammation, and supporting hormonal balance. This generally means prioritizing whole, fiber-rich foods, adequate protein at each meal, healthy fats, and minimizing refined carbohydrates and ultra-processed foods.

The Mediterranean diet and its anti-inflammatory variants have the strongest evidence base for PCOS management. They have been shown to improve insulin sensitivity, reduce androgen levels, and support more regular ovulation.

Foods That Tend to Worsen PCOS

Refined carbohydrates and sugars cause rapid blood glucose spikes that drive insulin surges and androgen production. Dairy and certain saturated fats may worsen inflammation in some women. Highly processed foods contribute to inflammatory load and gut dysbiosis.

Supplements With Evidence

Several supplements have meaningful research behind them for PCOS:

  • Myo-inositol and D-chiro-inositol improve insulin sensitivity and have been shown in clinical trials to support more regular ovulation
  • Magnesium supports insulin function and reduces cortisol
  • Zinc reduces androgen levels and supports skin health
  • Spearmint tea has demonstrated androgen-lowering effects in clinical studies
  • Omega-3 fatty acids reduce inflammation and support cardiovascular health

For a detailed PCOS meal plan and food guide, see: Best Diet for PCOS Weight Loss and Foods to Avoid With PCOS.

PCOS and Fertility

PCOS is one of the leading causes of anovulatory infertility — infertility caused by irregular or absent ovulation. However, a diagnosis of PCOS does not mean you cannot conceive. The majority of women with PCOS who seek fertility treatment are successful.

Natural Conception

For women with PCOS who are trying to conceive, the first approach is typically lifestyle-based. Even modest weight loss in women with insulin-resistant PCOS can restore more regular ovulation. Dietary changes that improve insulin sensitivity, stress reduction, and addressing nutritional deficiencies all support reproductive function.

Tracking ovulation in PCOS is more complex than for women with regular cycles, as standard ovulation predictor kits can give false positives due to elevated LH levels. Basal body temperature charting and monitoring cervical mucus are often more reliable approaches.

Medical Interventions

When lifestyle approaches are insufficient, several medications are used to stimulate ovulation:

  • Letrozole (an aromatase inhibitor) is now considered the first-line medication for ovulation induction in PCOS
  • Clomiphene citrate has been used for decades and remains effective for many women
  • Metformin can support ovulation by improving insulin sensitivity
  • In cases where these options do not work, IVF is an option with generally good success rates in women with PCOS

PCOS During Pregnancy

Women with PCOS have a higher risk of gestational diabetes, preeclampsia, and preterm birth. These risks are manageable with appropriate monitoring and care but make it important to inform your obstetric team of your PCOS diagnosis from the outset of pregnancy.

For a dedicated guide on conception with PCOS, see: Can You Get Pregnant With PCOS.

Treatment Options for PCOS

There is no cure for PCOS, but the condition is highly manageable. The most effective approach combines lifestyle changes with targeted medical support, tailored to your specific type and symptoms.

Lifestyle as First-Line Treatment

For most women, lifestyle changes are the most impactful and sustainable intervention:

  • A whole-food, lower-glycemic diet that stabilizes blood sugar and reduces inflammation
  • Regular exercise — a combination of resistance training (which improves insulin sensitivity) and moderate aerobic activity
  • Prioritizing sleep — poor sleep elevates cortisol and worsens both insulin resistance and androgen levels
  • Stress management — particularly important for adrenal PCOS, but beneficial across all types

Medications

  • Hormonal birth control regulates menstrual cycles and reduces androgen-related symptoms such as acne and excess hair growth
  • Metformin improves insulin sensitivity, supports more regular ovulation, and reduces androgen levels
  • Anti-androgens such as spironolactone reduce hirsutism and acne by blocking androgen receptors
  • Letrozole or clomiphene are used for ovulation induction in women trying to conceive
  • Inositol supplements (myo-inositol in particular) are increasingly used as a gentler alternative to metformin for insulin sensitization

Natural and Complementary Approaches

  • Spearmint tea — two cups per day has been shown in clinical trials to reduce free testosterone
  • Cinnamon — some evidence for improving insulin sensitivity
  • Acupuncture — limited but emerging evidence for supporting more regular ovulation
  • Gut health support — emerging research links gut microbiome health to PCOS severity

The right treatment combination depends on your type of PCOS, your primary symptoms, and whether fertility is a current goal. A collaborative approach with a gynaecologist or endocrinologist who understands PCOS is always the most effective path.

Long-Term Health Risks of PCOS

Left unmanaged, PCOS increases the risk of several serious long-term health conditions. Awareness of these risks is not meant to cause alarm — it is meant to motivate proactive management.

Type 2 Diabetes

The chronic insulin resistance at the heart of most PCOS cases significantly elevates the risk of developing type 2 diabetes. Regular blood sugar monitoring and lifestyle management are the primary tools for reducing this risk.

Cardiovascular Disease

PCOS is associated with an unfavorable cardiovascular risk profile — including elevated LDL cholesterol, reduced HDL cholesterol, higher blood pressure, and increased systemic inflammation. These factors combine to raise the long-term risk of heart disease and stroke, particularly after menopause.

Endometrial Health

When ovulation does not occur regularly, the uterine lining (endometrium) is not shed as it should be. Prolonged buildup of the endometrial lining increases the risk of endometrial hyperplasia and, over time, endometrial cancer. This is one of the reasons that regulating menstrual cycles — even if fertility is not a concern — is an important part of PCOS management.

Sleep Apnea

Obstructive sleep apnea is significantly more common in women with PCOS than in the general population, even after controlling for weight. This is thought to be linked to the effects of androgens on upper airway anatomy and respiratory control. If you experience persistent fatigue despite adequate sleep, snoring, or waking feeling unrefreshed, this is worth discussing with your doctor.

Metabolic Syndrome

Women with PCOS are at elevated risk of developing metabolic syndrome — a cluster of conditions including central obesity, high blood pressure, high blood sugar, and abnormal cholesterol levels that together significantly increase cardiovascular risk.

Polycystic Ovaries and Pregnancy

Having polycystic ovaries pregnancy is possible but can be more challenging due to irregular ovulation or hormonal imbalance. Many women with PCOS still conceive naturally or with the help of fertility treatments. Early diagnosis and treatment improve the chances of a healthy pregnancy.

Tip: Always consult a gynecologist or fertility specialist for personalized care.

Can You Get Pregnant with PCOS?

Yes, you can get pregnant with PCOS. While it may take more time or support, many people with PCOS go on to have healthy pregnancies. The key is understanding what might be affecting fertility and choosing the right approach to manage it.

Ovulation Issues

PCOS often affects ovulation due to hormonal imbalances. The ovaries may not release an egg regularly, which can lead to irregular or missed periods. Without consistent ovulation, it becomes harder to predict fertile windows and conceive naturally. However, ovulation is not always completely absent—it may just be irregular, which means pregnancy is still possible.

Treatment Options

There are several ways to improve fertility with PCOS, depending on individual needs.

  • Lifestyle changes such as maintaining a healthy weight, balanced diet, and regular exercise can help regulate ovulation
  • Medications may be prescribed to stimulate ovulation or improve insulin sensitivity
  • In some cases, fertility treatments like assisted reproductive techniques may be recommended

The right treatment plan can significantly increase the chances of conception.

Living Well With PCOS

PCOS is a long-term condition, not a temporary one. The goal is not to cure it but to manage it effectively enough that it no longer dominates your health or quality of life.

The women who manage PCOS most successfully tend to share a few consistent approaches. They treat food as medicine — not in a restrictive or punishing way, but by consistently choosing foods that support hormonal balance. They move their bodies regularly in ways that improve insulin sensitivity without further stressing the HPA axis. Also they take mental health seriously as part of the condition, not separately from it. And they work with clinicians who understand that PCOS is not a single condition with a single solution.

Perhaps most importantly, they give themselves time. PCOS does not respond to interventions overnight. Hormonal systems change slowly. The progress that comes from consistent lifestyle changes over three to six months is real and meaningful — but it requires patience that our instant-results culture makes difficult.

You are not broken. Your body is responding to signals that have become dysregulated. With the right information and the right support, those signals can be rebalanced.

What to Read Next

This guide is the foundation of the PCOS content on this site. Each link below goes deeper on a specific aspect of the condition:

Understanding PCOS

Symptoms

Causes and Triggers

Diet and Management

Fertility

Treatment

Frequently Asked Questions

Can PCOS go away on its own?

PCOS does not resolve entirely on its own, but symptoms can improve significantly — sometimes dramatically — with consistent lifestyle changes. Some women experience a natural reduction in symptoms after menopause, though the underlying hormonal and metabolic factors remain.

Can you have PCOS with regular periods?

Yes. Regular periods do not rule out PCOS. Some women have regular cycles but still have elevated androgens and polycystic ovaries on ultrasound. This is why diagnosis requires meeting the Rotterdam Criteria rather than relying on any single symptom.

Does PCOS always cause weight gain?

No. While weight gain is common in insulin-resistant PCOS, lean PCOS (sometimes called non-heavier person PCOS) affects women of normal or low body weight. The hormonal and metabolic disruptions are present regardless of weight.

Is PCOS genetic?

There is a significant genetic component. Having a first-degree female relative with PCOS roughly doubles your risk. However, genetics is not destiny — lifestyle and environmental factors influence whether and how severely PCOS expresses.

What is the best diet for PCOS?

There is no single universally best diet. The most evidence-backed approaches are anti-inflammatory and lower-glycemic — prioritizing whole grains, vegetables, quality protein, and healthy fats while minimizing refined sugars and highly processed foods. The Mediterranean diet has the strongest research support.

Can teenagers have PCOS?

Yes. PCOS can develop in adolescence, often around the time of puberty. Diagnosing PCOS in teenagers requires extra caution because irregular periods and some acne are normal during early puberty. A diagnosis in adolescents typically requires persistent symptoms over at least two years.

This guide is reviewed and updated regularly. Last updated August 2026. This content is for informational purposes only and does not constitute medical advice. Always consult a qualified healthcare provider for diagnosis and treatment.


Exit mobile version